Final Personnel Record for Newhouse, Delbert C., U.S. Navy, 1957
DOW-UAP-D104 · page 411 of 585
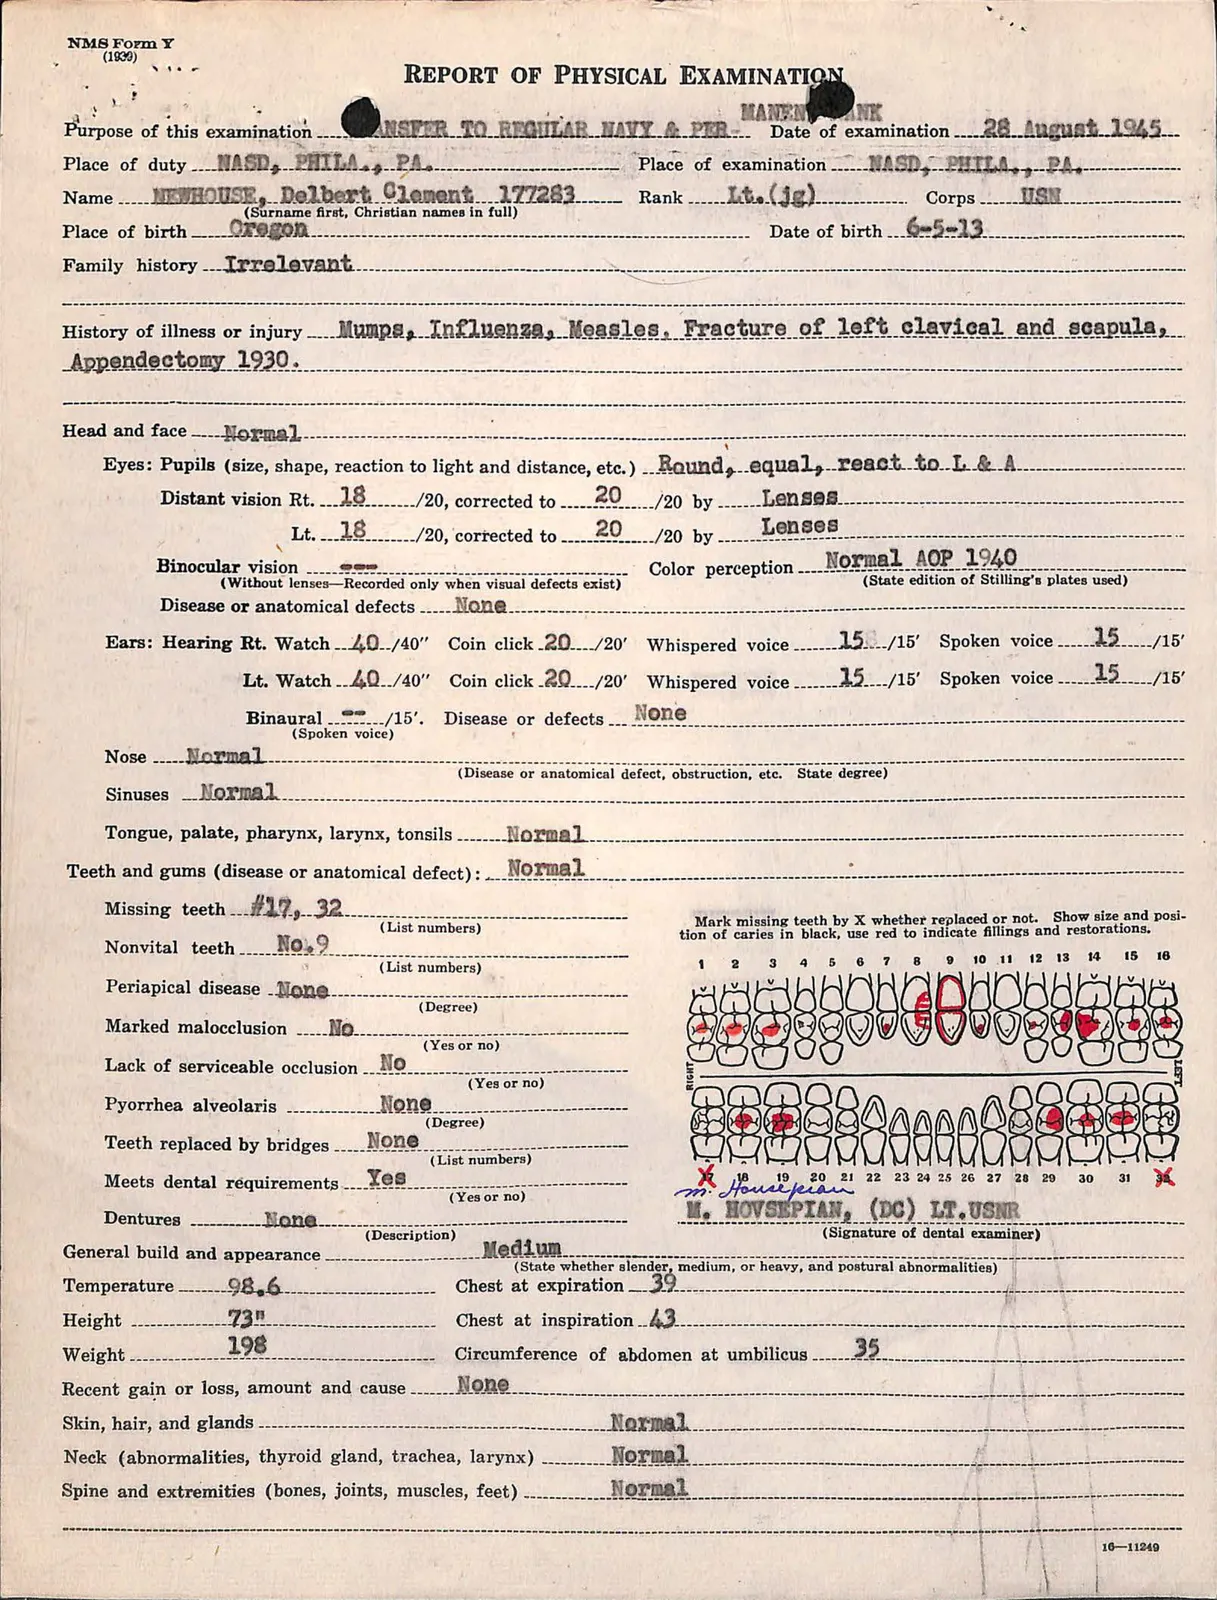
Text
This text came with the file. It may have mistakes. When the text and the image disagree, the image is right.
~
_ _
_ _
·
_
___
_
NMSFonnY
(19:l'.l)
.'
;
•. ~
.
_
REPORT OF PHYSICAL. EXAMINATI&
#ii. 1
. .
: . ' .A.u~
•.
, UANY.~
Nit . .
....a
,a,
rpose of this exam1pati~n ____•
..l.w..r...c.a._m..JmOUL.ML&ll..£:._.Pm:!__
Date of exarmnation ----.&IL--~~5___ ·
Place of duty -·--DASD.,...fflit..~.....-.~ .~ ---------·------------------ -Pia~~ of examination _.: ______$1);_.~._- i ..C...--------------·
Name ..___m!ffli'IDSR,,__J)_o.lher:t..Q.lo.aent._..1T.Z283_____ Rank .._.._L.t ..._{Jg.)______________. Corps------~
---·---·-·--------·
(Surname first, Christian names In full)
Place of birth _ __ oz.e,eo.n..-..··-·-·--··--·-------·--------------·-·------·--··-·--···--·-··--
Date of birth _.J,~s~lJ.________________.-·--·----·---
Family history ---lrr .elav.an.t..---.---·.---------·---·--·-----·-···___ ~ ~ .-·-····---...·-·-----·--·-·-..-------..---------------------------·-----·-----·
Hist~ry of illness or injury ____}JWJl~Ul#-__Infi1um~..,,_Jt~.§_EjJ ~ ~.l.- ~ ~~~~~--Qf__l~.!'!;__.QJ.,.~_yi_Q_~J___f!Q&l___~-~~..P-!A~,---·
Ap.pendectomy 1930.---··-------·--·---------·----------------·--·---·-----------·---·--·-----------------------------·-------------------------·--·-------·-
----------------------·-----·-----·-·-·----·---·----·----------·---------·------·-------------------·-····------···-·-------··------·---------------------------··----·
Head and face - --~r.ma.l.·--·-·-·-·-·-····------···-·:-._·_--·-···-·------·--·-··------··---------·--···------·-··--------·-··---··---··-···---·---~----------------·
.
\
Eyes: Pupils (size, shape, reaction to light and distance, etc.) _...aciund~_.equa4_.rea.0t...to_.L._&.._A______________ ____.._.__.
Distant vision Rt. ___lff_._____./20, corrected to -----~_9__ ..../20 by -·-···-Lenses__. _.....__,..._.___·_··--------------------·-··--·-
Lt. __J ,a_._____./20, ·corrected to --·--~-Q.____/20 by _.._.J'.~~!!~~~----------··---------·---------------------·--·-··---·•
'
Binocular.visic:m ____.!f!.~·-···----·--:--··---·------·---·--------
Color perception ____]J_Q.!:l!!.~l.-~~~-J9-i Q--------------·----------
(W,thout lense!t-Recorded only when visual defects exist)
(State ed1llon of St,lling'a plates used)
Disease or anatomical defects ____..None.....-·--·---··-········-··-···-·····------·-----··---------·-------------------------·----···---------·--·
Ears: Hearing Rt. Watch __.4Q__/ 40" Coin click _2O___.f20' Whispered voice _______l5~_..fl6'
Spoken voice ---···15.-··-·/16'
Lt. Watch __,40../40" Coin click _20..../20' Whispered voice -··--·_.l5____/ l6' Spoken voice -·----l 5...___.fl6'
Binaural _.:".'.:".'..../15'. Disease or defects ___ N o n e·--···--··-·-·-------·-··--··---·---··-··----·· --·---··----------------··-----·
(Spoken voice)
,
Nose -----!lor.mal.----..__·-..·--·.----·_·-·-..._.·--.._·-....................._____..._....._·--·..______·--·--·-..·----··-·-------------.--.-·---.·-.·----·•----.
(Disease or anatomical defect, obstruction, etc. State degree)
Sinuses _Normal.---------- -------------------------------- ----- -------·-------------------.---------------------------------------------------------------- - --
Tongue, palate, pharynx, larynx, tonsils -·-----llormsJ..__·-···-------------------··-------------------------·---·---------------------··--····-····
Teeth and gums (disease or anatomical defect) • ~--Normal _·-·-- ------------·-----------·--------· · ·--------------------------- --·-----------------·
Missing teeth _..IfJll.,..J2.._____·-.......______·--.________·-----------
Mark missing teeth by X whether re'lllaced or not. Show size and posi
<List numbers)
tion of caries in black, use red to indicate fiOings and restorations,
Nonvital teeth ---·- No:.9.·--·--·--······---·-····-··-----------------
(List numbers)
1
2
s
4
5
e
7
8
11
10 ti
IZ
13
14
15
16
Periapical disease -llone.----~·---··---<n-;~~;;;>-·--------··-------·---
!ii~· i@cij§@.~~·e.rt9_~~ijivi§
Marked malocclusion ____.ND--·----·---·------······--------·--·--·-·-
~. ij w
ij l\:/
(Yes or no)
Lack of serviceable occlusion -·-~ 9-----·--·--···------·-·-·----------
<Yes or no)
~~~~
"~@i@.~@aeeee8§
Pyorrhea alveolaris ·-------·--·--·NQn,n;ir;~ ->-·-·-------------------
. . .
Teeth replaced by bridges----·N one·-········-······-·-··--------
<List numbers)
24
2
:eets dental requirements ____°X~~----···(y·;;~-,_·;~)---··-----------
-
~ gf~J~
3;.o::
3
)
~;:~~
•
9
3o
31
}(
entures _
Jilone -------------·-··-·---·----------------------
·-----------------·---··--:!----------·---····-·--------------·----------------
<Description>
(Signature of dental examiner)
General build and appearance -·-------------···-----·lle.di um._________________._____········-··---------.--·-----·--·------··------·· ---------------·--··--·
.
(State whether slender medium, or heavy, and postural abnormalities)
Temperature ------.98...6.------------------------
Chest at expiration __3 _9__·---·------·------··----------------·--·-·--------{-----------·-------·---·----
Height _______________73" _____ _.·----------·----
Chest at inspiration ..4'J..____________.·--·-----------------·-----------·--·------------------------·---·
Weight -----·--·----·J.,9~-·-·-·---------·---------·-
Circumference of abdomen at umbilicus ____..J~--------------------- , _________________________
Recent gai_n or loss, amount and. cause __•_____tl_Q.t:l~----------------------------------·----·--·-----------------·----------------------:-----·--------------
l
Skin, hair, and glands --·-.·-.-·---•••-·.--·-·-.·---·------...--·-·----___.___Normal__________._______·----.---------------------------------------------·------
Neek (abnormalities, thr roid gland, trachea, larynx ) ___________NQf_~).___ __.________·---------- ------------------:--------!;----------------------
Spine and extremities (bones, joints, muscles, feet) _______ _______N9X~1.__________________________________________________,__________..-----·-----
1